
Lahalak Medical PlatformDifferentiate Care
Learn the differences between marginal and velamentous umbilical cord insertion, and vasa previa, including diagnosis, risks, and clinical management.
Advertisement
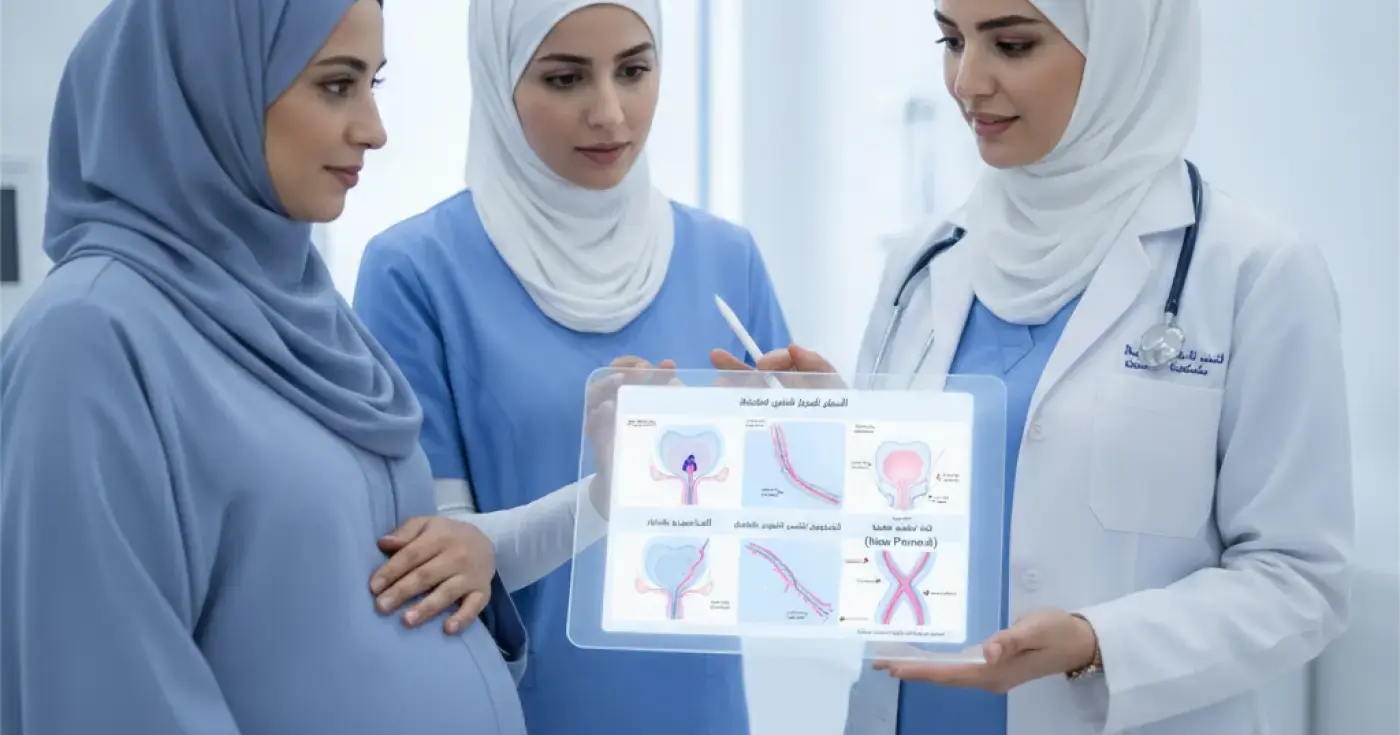
Umbilical cord insertion describes the site where the cord connects to the placenta. The connection may be near its margin, or some vessels may run within the membranes before reaching it, which differs from vasa previa, where fetal vessels pass near or over the cervix. Ultrasound, and sometimes transvaginal imaging with color Doppler, determines the nature of the condition and the appropriate plan.
In normal pregnancies, the umbilical cord inserts into the main body of the placenta, typically near the center (central or eccentric insertion). This structural arrangement ensures that the fetal blood vessels, which carry oxygen and essential nutrients, are fully protected within the cord and surrounded by a gelatinous substance called Wharton's jelly until they directly enter the placental tissue. This normal insertion protects the delicate vessels from compression or tearing during fetal movements and uterine contractions.
Marginal umbilical cord insertion occurs when the cord attaches to the outer edge of the placenta (less than 2 cm from the margin) rather than the center. This is sometimes referred to as a "battledore placenta." In this scenario, the blood vessels remain protected by Wharton's jelly, but the peripheral attachment can make them slightly more vulnerable to mild compression. This condition is commonly detected during a routine second-trimester FSCAN (fetal anomaly scan). It is relatively common, rarely causes significant complications, and usually allows for a safe vaginal delivery unless other obstetric indications arise.
Velamentous cord insertion is a more delicate anatomical variation where the umbilical cord does not insert directly into the placenta. Instead, it inserts into the fetal membranes (amniochorionic membranes). Consequently, the fetal blood vessels must travel unprotected by Wharton's jelly through the membranes to reach the placental edge. This leaves these sensitive vessels vulnerable to compression or rupture, particularly when the membranes rupture (water breaks) during labor. Velamentous cord insertion requires careful ultrasound monitoring of fetal growth to ensure adequate blood flow.
Vasa previa is a rare but high-risk obstetric condition that is distinct from simple marginal or velamentous insertion, though it can sometimes result from the latter. In vasa previa, unprotected fetal blood vessels run through the membranes directly over or within 2 cm of the internal cervical os (the opening of the cervix). The critical danger is that these vessels lie directly beneath the presenting part of the fetus. Any cervical dilation or rupture of membranes can tear these vessels, leading to rapid, life-threatening fetal hemorrhage.
Obstetric ultrasound is the primary diagnostic tool for identifying the umbilical cord insertion site. During the routine mid-pregnancy anomaly scan, the sonographer evaluates the cord's insertion point into the placenta. If a marginal or velamentous insertion is suspected, it is documented for ongoing clinical surveillance. Ultrasound screening helps rule out any overlying vessels near the cervix, ensuring early detection and proper care planning.
If velamentous insertion or vasa previa is suspected, clinicians utilize transvaginal ultrasound combined with color Doppler imaging. Transvaginal ultrasound provides high-resolution views of the cervix, while color Doppler visualizes active blood flow, allowing the clinician to clearly identify any fetal vessels crossing the cervix. This level of detail is crucial and cannot always be achieved via transabdominal ultrasound alone.
Velamentous and marginal insertions require periodic ultrasound monitoring to assess fetal growth and rule out intrauterine growth restriction (IUGR), as abnormal cord insertion can occasionally affect nutrient transfer efficiency. Monitoring includes measuring fetal biometry, amniotic fluid volume, and umbilical artery Doppler flow. If fetal growth remains stable and Doppler indices are normal, routine prenatal care continues without invasive intervention.
For simple marginal cord insertion, physical activity and sexual intercourse are typically not restricted. In cases of velamentous cord insertion, mild activity modification may be advised. However, if vasa previa is diagnosed, or if there is coexisting placenta previa, pelvic rest (avoiding intercourse and strenuous activity) is strictly recommended to prevent any mechanical pressure or friction that could trigger catastrophic bleeding.
The birth plan depends entirely on the precise diagnosis, placental location, and vessel positioning:
Any vaginal bleeding or sudden rupture of membranes in the second half of pregnancy is a medical emergency, especially if the patient has a known or suspected diagnosis of vasa previa or velamentous insertion. Because the bleeding may originate from fetal circulation, immediate clinical intervention is vital to safeguard the baby's life.
| Feature | Marginal Insertion | Velamentous Insertion | Vasa Previa |
|---|---|---|---|
| Insertion Site | At the placental margin (less than 2 cm). | Into the fetal membranes, away from the placenta. | Into the membranes, with vessels crossing the cervix. |
| Vessel Path | Fully protected by Wharton's jelly. | Unprotected vessels run through membranes to the placenta. | Unprotected vessels run directly over the internal os. |
| Primary Diagnostic Tool | Routine transabdominal ultrasound. | Detailed anomaly scan and color Doppler. | Transvaginal ultrasound with color Doppler. |
| Clinical Follow-up | Standard fetal growth monitoring. | Serial growth scans and Doppler assessment. | Close surveillance, potential hospitalization. |
| Impact on Delivery Plan | Vaginal delivery is usually planned. | Vaginal delivery is possible with close monitoring. | Planned cesarean delivery is mandatory (34-37 weeks). |
Short answers that help clarify the key points related to this article.
Advertisement
Helpful services
Subscribe for new educational pregnancy and birth content from LahaLak.
Compare hospitals and prices by city and birth type, then continue to booking with clear steps.
From LahaLak guide
Medical article
Learn about single umbilical artery (SUA) on ultrasound, the difference between isolated and non-isolated cases, and fetal growth monitoring.
Read article
Medical article
A comprehensive medical guide on umbilical cord blood banking in Saudi Arabia. Learn about public donation, private storage, costs, and medical uses.
Read article
Medical article
Discover the health benefits of delayed umbilical cord clamping for newborns, its role in birth plans, and when immediate clamping is medically required.
Read articleConnected next steps
 Customized Fetal Growth Velocity ChartingEnsure your baby's optimal development with advanced customized growth charts that adjust for maternal characteristics, providing superior accuracy in identifying growth risks compared to standard population-based charts.
 Fetal Liver Biometry and Metabolic Assessment UltrasoundA specialized ultrasound assessment measuring fetal liver volume to evaluate nutritional status. This advanced screening helps detect growth disturbances and metabolic issues early, ensuring optimal prenatal care and fetal well-being.
 Fetal Cardiac Output Doppler AssessmentAdvanced Doppler assessment of fetal heart health, ensuring precise monitoring of blood flow and hemodynamics for healthy growth and early intervention if needed, providing you with absolute peace of mind.
 Parvovirus B19 (IgG/IgM) Antibody TestA vital screening for pregnant women exposed to the virus, detecting antibodies to prevent complications like fetal anemia or hydrops, ensuring a healthy and safe pregnancy journey.